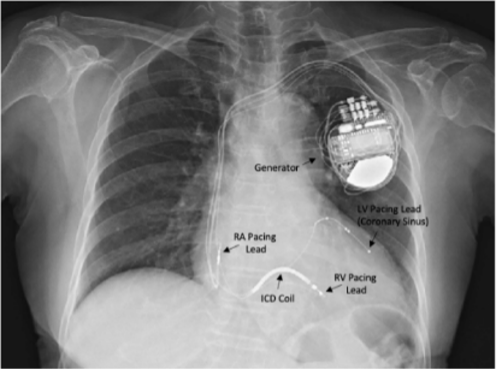
Cardiac Devices
Mert Demirci
PPMs
- Can be single chamber (RA or RV), dual chamber (RA and RV) and biventricular (RA+RV+coronary sinus).
- Codes for pacing modes: usually three-four letters such as AAI, VVI, DDDR
- 1st letter: chamber(s) paced (O: none, A: atrium, V: ventricle, D: dual (A+V))
- 2nd letter: chambers sensed (same as above)
- 3rd letter: what pacer does when senses (O: none, T: triggered, I inhibited, D: dual (T+I)
- 4th letter: Either O or R. R: rate modulation 43 CARDIOLOGY
Example: AAI pacer-> paces the atrium(A) and senses atrium(A) and inhibits (I) pacing output when a native atrial signal is sensed -> can be used in SN dysfunction DDDR: Senses and paces both the atria and ventricle. If beat not sensed within a predefined interval, beat delivered. R indicates rate responsivity (changes rate based on changes in pt activity)
1. Permanent pacemakers (PPM)
A device that maintains or restores a normal heart rhythm by stimulating the myocardium.
Indications: (class 1 indications below, refer to ACC/AHA guidelines for class 2 and 3)
- Sinus node dysfunction (bradycardia with or without sinus pauses, tachy-brady syndrome). Indication is symptom driven, there is no established minimum HR or pause duration.
- AV block:
- Mobitz II , 3rd degree block -> regardless of symptoms
- Mobitz I: if symptomatic
- Other conduction diseases:, Alternating bundle branch block, Neurocardiogenic syncope
Leadless pacemaker (Micra): Self-contained devices implanted in RV endocardium, has lifetime 12-15 years. New devices can also be implanted dual chamber (RA,RV) and provide DDD pacing (Aveir DR). Can be suitable for patients who has poor upper extremity venous access, high infection risk (HD, prior device infection) or limited life expectancy
2. Implantable Cardioverter/Defibrillators (ICDs)
Device with defibrillation coil +/- pacing lead, which can detect and treat VT/VF, can terminate arrythmias with anti-tachycardic pacing (ATP)- attempts to pace out of VT to prevent a shock, and can defibrillate if ATP unsuccessful
Indications:
- Primary prevention (expected survival >1 year)
- HFrEF
- EF <35% and NYHA II-III or EF <30% and NYHA I
- Must be >90d from revasc, >40d from MI, and on GDMT >90d if non-ischemic
- Arrhythmogenic syndromes: Arrhythmogenic RV cardiomyopathy, Brugada syndrome, HCM and cardiac sarcoid with specific risk factors
- HFrEF
- Secondary prevention
- Prior cardiac arrest due to VF/pVT (not from reversible cause)
- Spontaneous sustained VT
- Inducible VT on EP study with history of syncope
3. Cardiac Resynchronization Therapy (CRT)
- BiV pacer that coordinates LV/RV contraction through synchronized activation of each ventricle following atrial contraction. Increases LVEF and induces LV reverse remodeling
- Indications (Class I):Patients with NYHA II-III or ambulatory IV + LVEF ≤ 35%+ Normal sinus rhythm + QRS >150ms with LBBB
- Can be either CRT-P (pacing only, no defibrillation) or CRT-D (pace+defib)
PPM Complications
- After placement: Pocket hematoma and infection, myocardial perforations and cardiac tamponade, infection, lead displacement
- Long term complications: Device infection, lead fracture (lead lifetime 10-15 years), insulation failure, VTE, lead related TR, inappropriate shocks due to missensing.
Practical tip: The Pacemaker ID app is free and is useful for identifying device brand for interrogation When differentiating PPM vs. ICD, look for a coil and charge generator to identify the ICD.