Behavior (hallucinations or delusions, restlessness or agitation, psychomotor abnormalities, sleep disturbances).
Cognition (impaired memory, deficits in attention, disorientation, disturbances in speech).
Delirium can persist despite identification and reversal of underlying causes, particularly in older patients or those with baseline cognitive deficits.
Evaluation
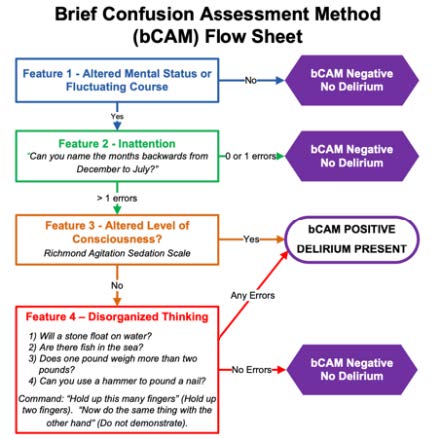
Use screening tools to assess for delirium: Brief Confusion Assessment Method (bCAM). See critical care section for the ICU version, CAM-ICU.
Example attention tasks: “Please name the months/days backwards starting from XX?”
Mnemonic for common causes of delirium:
D- Drugs/toxins (use of benzodiazepines, opiates, anticholinergics, steroids, etc., withdrawal from ETOH, benzos, etc.)
E- Eyes/ears (sensory deficits)
L- Low perfusion states (MI, PE, heart failure, sepsis)
Are changes needed to address pain control, constipation, insomnia, nausea, etc?
Substance use – evaluate for EtOH or BZD withdrawal state.
EEG – evaluate for seizures, confirm presence of encephalopathic changes.
LP – if concerned for CNS infection, inflammatory condition.
Management
If able to identify underlying cause: treat as above.
Empirically load on thiamine (500mg IV tid x9 doses).
Cognitive impairment or disorientation.
Provide clock, calendar, and appropriate lighting.
Regular reorientation
Provide cues from a familiar environment (pictures, calls or visits from family members).
Ensure hearing aids, glasses, and dentures are available.
Maintain normal sleep-wake cycle.
Keep lights on in the day and avoid excessive naps.
Early PT, OT interventions, mobilization, move to bedside chair when able.
Remove medical support devices as able (foley catheters, restraints, telemetry).
Ensure adequate bowel regimen and hydration.
Assess for pain and treat appropriately.
Medication reconciliation to reduce or eliminate total anticholinergic load, and to reduce or eliminate other deliriogenic medications as able.
See critical care section for prevention in the ICU (ABCDEF bundle).
Note on pharmacologic management: There is no pharmacologic intervention known to prevent or treat delirium. Medications for agitation only treat certain behavioral symptoms of delirium, are typically ineffective/harmful for hypoactive delirium, and do not modify the underlying pathological process. Reserve medications for agitation impairing patient safety when non-pharmacologic interventions alone are unsuccessful. See agitation section for medication approach.