
Opioids: General Principles and Conversion
AJ Winer
Overview
Frequently used for acute pain. Limit use as much as possible in chronic pain as it contributes to long-term central sensitization.
For patients on chronic opioids at home, you should continue opioid therapy while inpatient to prevent withdrawal, but can titrate the dose as needed.
When discharging on opioids:
- Ensure pt is prescribed naloxone unless in an excluded population (i.e. palliative).
- If on high OME, refer to pain clinic or palliative care depending on opioid indication.
- Ensure pt is discharged with enough opiate to make it to next outpatient appointment (usually ~1-2 weeks).
Common choices for acute pain in hospital (always start at low end for opioid naïve):
- Oxycodone (PO) 5-10mg q4 to 6 hours prn.
- Hydromorphone (IV) 0.25 to 1mg q2 to 3 hours prn.
Use OME (oral morphine equivalents) to transition between opiates, reduce OME by 1/4 to 1/3 to account for cross tolerance.
- Example: if switching from oxycodone 10mg q4h PRN to morphine ER q12h, calculate 24H OME = 60 (total mg in 24h) x 1.5 (conversion) = 90 OME. Reduce by 25-33% = ~60-67.5 OME = morphine ER 30mg q12h.
To up titrate: increase dose by 25-50% for moderate pain (4-7/10) and 50-100% for severe pain (8-10/10).
When a patient is requiring 4-5 PRN doses/24h, consider starting long acting.
- The ER medication should treat the chronic pain experienced by a pt. The IR preparation is for breakthrough pain. Each IR dose should be ~10-20% of the total OME dose a pt takes daily.
- Example (using above case): total OME 90. 10-20% = 9-18mg is ~15mg. Divide by 1.5 (converts back to oxycodone which is 1.5x as strong) = oxycodone 10mg q4h PRN breakthrough.
When converting from oral to fentanyl patch, divide 24h OME by 2 or 3 gives ~dose of fentanyl patch in mcg/hr q72h.
To calculate VUMC pt’s 24-hour OME: Go to Pt Summary then pain and sedation tab or morphine equivalence tab.
Other:
- Tramadol: Has opioid and NSAID properties but also inhibits serotonin and norepinephrine reuptake. Metabolized by CYP3A4 and CYP2D6 so there is variability between pts. Typical dose: 25 to 50mg q4 to 6 hours PRN.
- Buprenorphine:
- Sublingual (Subutex, suboxone), buccal (Belbuca), transdermal (Butrans).
- Increased affinity to mu opioid receptor leads to slower disassociation and prolonged analgesia. Preferably acts on spinal receptors (vs CNS).
- Can precipitate withdrawal from opioids at high doses.
Oral morphine equivalent (OME) conversion table
| Drug | PO | IV | APAP | IR | ER | Notes |
|---|---|---|---|---|---|---|
| Tramadol | 0.1x | - | - | Tramadol | Ultram ER™ | NSAID properties |
| Morphine | 1x | 3x | - | Morphine IR | MS-Contin™ | Renally cleared |
| Hydrocodone | 1x | - | Lortab | Hydrocodone | NA | |
| Oxycodone | 1.5x | - | Percocet | Roxicodone™ | Oxycontin™ Xtampza |
|
| Hydromorphone | 4x | 12.5* | - | IV, Oral | - | Oral is $ |
| Fentanyl | 200-300x | 200-300x | - | IV, Buccal, Nasal | Patch | Dosed in ug, not mg |
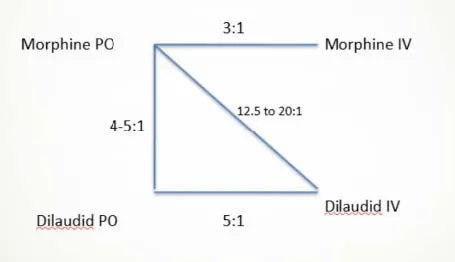
Abbreviations: ER, extended release; IR, immediate release; IV, intravenous; PO, oral; APAP, Acetaminophen *Note: IV Hydromorphone conversion previously was 20:1. Based on recent data, this has been changed to 12.5:1, but some providers may still use 20:1.
Opioid pharmacokinetics
Mechanism | Onset | Peak Effect | Duration |
|---|---|---|---|
| PO | 30 min | 1 hr | 3-4 hrs |
| IV | 5-10 min | 15 min | 1-2 hrs |
Buprenorphine Pharmacokinetics
Route |
Brand Name |
Onset of action |
|---|---|---|
| Sublingual | Subutex, Suboxone | 30-60 min |
| Buccal | Belbuca | 30-60 min |
| Transdermal | Butrans | 18-24 hours |
Buprenorphine Conversion to OME

Pt Controlled Analgesia (PCA)
Pumps can be programmed to deliver a continuous rate and/or a bolus dose.
The general rule of thumb is to calculate the total OME delivered through the demand when a pt is in steady state and convert 75% of this dose into the total continuous rate.
Basal rate: continuous infusion dosed per hour that cannot be adjusted by the pt.
- Calculate OME for 24 hour period and convert to IV medication (hydromorphone, morphine, fentanyl) and divide by 24 hours to get an hourly rate. If moderate pain, increase dose by 25-50%; if severe, by 50-100%
Demand doses: a pt-directed bolus that is given at a prescribed frequency whenever the pt presses the button. Both the dose and frequency can be adjusted.
The bolus doses combined should be 10-20% of total daily dose. Adjust the availability based on how frequently you want pt to be able to have a demand dose (often q10min to q30min).
- Don’t forget to set lockouts (maximum dose that can be given over a certain period of time) that includes both basal and demand doses.
Remember that the basal rate will not get to steady state for at least 8 hrs. When you admit pts or are transitioning to a PCA, always initiate the PCA pump with a bolus (or loading) dose.
How to order PCA at VUMC
- Select Analgesic:
- *Hydromorphone (most common): Order “Hydromorphone (DILAUDID) PCA."
- Fentanyl (if on at home; not a good inpt PCA): Order “Fentanyl PCA."
- *Morphine: Order “Morphine PCA” à pick from 3 different concentrations (mg/mL = 1:1, 5:1, 10:1). 1:1 is often suggested for start. 5mg/mL for pts requiring more than 60mg/24h. 10mg/mL for pts requiring more than 300mg/24h. Avoid in renal impairment).
- Select “[Analgesic] PCA syringe” and adjust the following to pt’s needs:
- PCA Dose (“Demand”): amount delivered when button is pushed.
- Lockout Interval: time between each “demand” dose.
- Continuous Dose (“Basal”): amount per hour given regardless of button pushes.
- Max Dose: maximum amount of analgesic (Basal + Demand) pt can get in 24 hours.
How to Order PCA at VA
- Under Orders, select “Pain/Sedation Infusions.”
- Under “PCAs,” select Analgesic of choice (Hydromorphone or Morphine).
- Adjust the following:
- Load: amount the pt will receive on initial set up of PCA.
- Basal: amount the pt gets per hour in continuous infusion.
- Demand: amount the pt gets when s/he presses the button.
Interrogating PCA (to determine amount of analgesia pt received)
- Select “Channel Select” on PCA IV pump.
- Select “Options” in bottom left of IV pump.
- Select “Pt History” on the left of the screen. This shows the administration history for a certain time period (e.g., 24h, 12h, 4h, etc.)
- Hit “Zoom” on bottom of screen to change time period to 24 hours.
- Total Drug: total amount of drug received in last 24 hours.
- Total Demands: amount of times the pt had pushed the button for demand dose.
- Delivered: amount of times the pt actually received a demand dose.
- The difference between “Total Demands” and “Delivered” is the number of times the pt pushed the button without receiving a dose.
- If you have questions about interrogating the PCA, ask your patient’s bedside RN.
Opioid side effects
- Constipation: Dose-dependent and will not develop tolerance. Order robust bowel regimen (MiraLAX, senna) with goal of BM ≥every 3 days.
- For opioid-specific constipation: SQ RelistorTM (methylnaltrexone), but this is expensive.
- For pts with chronic opioid-induced constipation: MovantikTM (NaloxgeolTM).
- Can also consider PO naloxone but it does have small amount of bioavailability so watch for systemic reversal.
- Nausea: Occurs with opiate naïvety. Consider starting an anti-emetic concurrently. Most pts will develop tachyphylaxis with this over a day, so the antiemetic can be discontinued.
- Urinary retention: Consider role of opioids in pts with new-onset or worsening urinary retention. Try to de-escalate opioid dosing if possible.
- Overdose: In pts with apneic emergency, IV 0.4 mg Naloxone; repeat multiple doses until response.
- Order naloxone 4 mg intranasal for outpatient opioid therapy.
- If a pt with chronic opiate dependence is over sedated but not in immediate danger of respiratory failure, one can 1) hold the dose of opioid and let them wake up on their own or 2) give a dose of naloxone 0.02-0.04mg (1/10 of the usual dose, ask the nurse to dilute 0.4mg in 10cc NS and push one cc at a time). This latter strategy prevents opioid withdrawal and precipitation of pain crisis in pts on chronic opioids.
- Pruritis: Due to histamine release from mast cells; treat with antihistamines. The opioid can also be rotated. Some but not all pts will develop tachyphylaxis.
- Toxicity: Hyperalgesia and neuroexcitatory effects (AMS, myoclonic jerking, seizures). Risk factors for neuroexcitatory effects are rapid titration, dehydration, and/or renal failure.