Tracheostomy
Alice Kennedy
Indications for Tracheostomy
- Prolonged mechanical intubation and weaning
- Failed extubation attempt(s)
- Tracheal stenosis
- Upper airway obstructions (e.g., head and neck cancers, severe infections, congenital)
- Trauma
- Neuromuscular disease
Benefits of Tracheostomy vs ET tube
- Lower risk of laryngeal and vocal cord damage.
- Improved communication (i.e. speaking valve).
- May be able to eat.
- Improved comfort and decreased need for sedation.
- Lower airway resistance -> reduced work of breathing
- May reduce time to wean from the vent and hospital LOS (mixed data).
- Potentially improved patient mobility.
- Easier access to trachea for suctioning/airway hygiene.
- May decrease risk of ventilator associated pneumonia (mixed data).
- *Note: No proven reduction in short-term mortality.
Timing of Tracheostomy
- Generally performed after 2 weeks of intubation.
- Earlier tracheostomy considered for anticipated prolonged mechanical ventilation.
- Research: No benefit in 30-day mortality rates or hospital length of stay for early (day 4) vs late (day 10) tracheostomy in TracMan trial (Tracheostomy Management trial, 2013).
- *Note: Many patients in late trach group did not end up requiring one.
Tracheostomy Tubes
- Most common in VUMC = Portex.
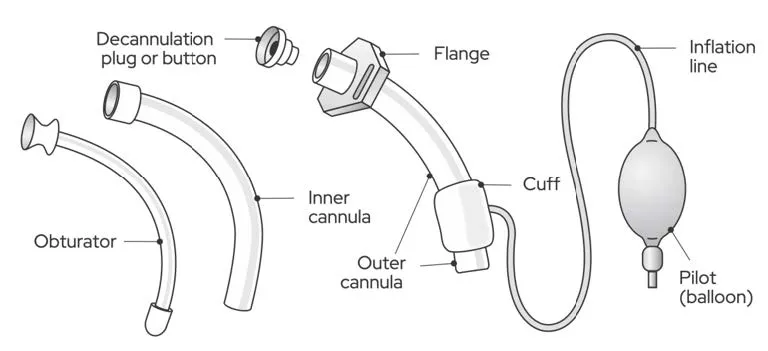
- Components:
- Faceplate/Flange: Secures tube in place, lists model and size.
- Inner cannula: Can be removed, cleaned, and replaced.
- Cuff (optional): Allows for pt to be ventilated; may prevent aspiration. Pressure needs to be assessed qshift and kept <30mmHg.
- Fenestration (optional): Allow speaking without valve.
- Obturator: Kept at the bedside, assists with trach insertion/removal.
- Sizes:
- Typical initial: 8-0; downsized to: 6-0 (Portex sizes comparable to ETT).
- Lengths: Standard vs. Extra-long (XLT-P = longer proximal end, XLT-D = longer distal end).
- Presenting rounds = size/cuff status/brand (e.g. 8-0 cuffed Portex)
- “Trach collar” means patient is receiving humidified O2/room air, cuff is down.
Speaking Valves
- Passy Muir Valve (PMV): One-way valve allowing air through the trach during inhalation, and forcing air up around the trach and through the vocal cords to allow for phonation.
- Contraindications: Upper airway obstruction, copious secretions, decreased cognition, severe medical instability, or inability to tolerate cuff deflation.
- *Cuff must be deflated when PMV is on since air needs to be able to travel around the tracheostomy and through the pharynx for the patient to exhale. Must remove when asleep.
Maintenance of Tracheostomy Tubes
- Inner cannula should be cleaned 2-3x per day or swapped.
- Daily stoma care to prevent pressure ulcers and infections.
- As needed suctioning for secretions.
Complications and Airway Emergencies in a Tracheostomy Patient
- Hemorrhage (mild bleeding from surface vessels and granulation tissue is common, major bleeding is rare –i.e. erosion into innominate artery).
- Causes for alarm: Drop in sats/Hgb, new tachycardia or hypotension, increasing PIP, new/worsening bleeding, or large clots.
- Airway damage - subglottic or tracheal stenosis, tracheobronchitis.
- Fistulas (tracheoarterial, tracheoesophageal).
- Unintended tracheostomy tube dislodgement
- All pts with trachs have a yellow sign above bed with date, type, size of trach as well as a replacement trach with obturator in the room.
- Fresh trach (≤ 14 days): do NOT replace due to risk of misplacement into the mediastinum and loss of airway; manage airway from above.
- Older trach: can be replaced at bedside with obturator.
- In the case of an EMERGENCY:
- Bag mask (use hand/gauze to occlude stoma) or intubate from above; except if complete laryngectomy then use stoma.
- Contact Surgical Airway Emergency Team +/- Team that placed it.
Secretion Management
- Respiratory hygiene: heated vent, consider guaifenesin, hypertonic saline, DuoNebs, cough assist device, appropriate suctioning, acapella, IS
Decannulation
- Candidates: Must protect their airway and be on minimal FiO2 settings.
- Should pass capping trials and tolerate PMV for most of the day.
