
Dementia
Samuel Heery
Normal Aging | Mild Cognitive Impairment (MCI) | Major Neurocognitive Disorder 2/2 Alzheimer’s Dementia |
|---|---|---|
|
|
|
| Cognitive domains: learning/memory, language, executive function, complex attention, perceptual motor, social cognition | ||
Major Neurocognitive Disorder Due to: | Alzheimer’s Disease | Vascular Dementia | Lewy Body Dementia | Frontotemporal Dementia |
|---|---|---|---|---|
| Onset | Gradual | Sudden or stepwise | Gradual | Gradual (age < 60) |
| Cognitive Domains & Symptoms | Memory, language, visuospatial | Depends on location of ischemia | Memory, visuospatial | Executive dysfunction, personality changes, disinhibition language, +/- memory |
| Motor Symptoms | Rare early; Apraxia later | Correlates with ischemia | Parkinsonism (memory loss typically precedes) | None |
| Progression | Gradual (over 8-10 years) | Gradual or stepwise with further ischemia | Gradual, but faster than Alzheimer’s disease | Gradual, but faster than Alzheimer’s disease |
| Imaging | Possible global atrophy | Cortical or subcortical on MRI | Possible global atrophy | Atrophy in frontal & temporal lobes |
Rare causes of dementia: Parkinsonian’s disease dementia, posterior cortical atrophy, CJD, corticobasal degeneration, neurosyphilis, NPH, autoimmune dementias (eg, NMDA)
Evaluation
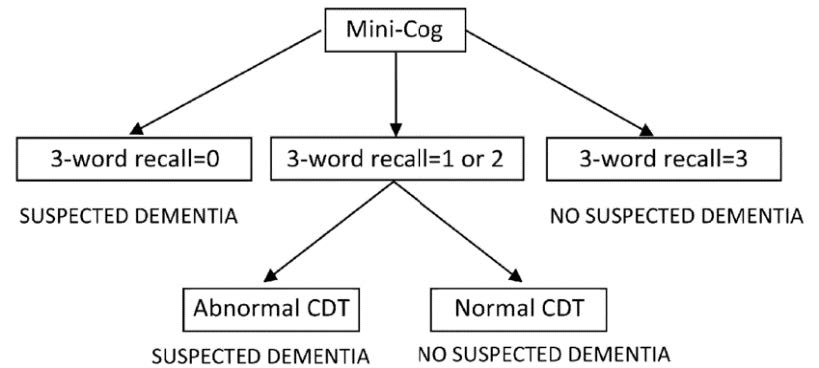
MINI-COG: Screening test for cognitive impairment (highly sensitive)
MOCA: Montreal Cognitive Assessment
- Lengthier test of cognition (but highly specific for cognitive impairment), MUST be done by someone who is certified
- Useful for detecting subtle deficits as in MCI
- Training and Certification is mandatory for proper use.
- Scores:
- 18-25: Mild
- 10-17: Moderate
- <10: Severe
- Rule out reversible causes of dementia-like symptoms: DEMENTIA
- Drugs
- Emotional (depression)
- Metabolic (CHF, COPD, CKD, OSA)
- Endocrine (hypothyroidism, hyperparathyroidism, hyponatremia)
- Nutrition (B12 deficiency)
- Trauma (chronic SDH)
- Infection (RPR)
- Arterial (vascular)
- Consider referral for Neuropsychiatric testing for unclear diagnosis. MRI brain with contrast is tier 1 testing as workup for cognitive behavioral syndrome.
Management
- Targeting Cognitive Impairment
- - Cholinesterase Inhibitors Donepezil, rivastigmine, galantamine (Reference)
- Indicated for any stage of AD, PDD, LBD, Vascular Dementia (avoid in FTT)
- Does not prevent dementia
- SE: GI (nausea, diarrhea), bradycardia, orthostasis
- - Cholinesterase Inhibitors Donepezil, rivastigmine, galantamine (Reference)
- NMDA Antagonists: Memantine (Reference)
- Indicated in moderate to severe AD alone or in combination with cholinesterase inhibitors
- Fewer SE than cholinesterase inhibitors
- Anti-amyloid Modulators: lecanemab and donanemab
- FDA approved for MCI or mild AD
- Reduce brain amyloid levels: 27-40% slower rate of cognitive decline
- SE: cerebral edema
- Requires referral to neurology at VUMC
- Targeting Behaviors
BPSD: Behavioral and psychological symptoms of dementia- Non-pharmacologic management (best evidence): treat underlying cause, hydration/nutrition, orient, mobilize, manage pain, engage family, sleep
- Depression: Antidepressants (SSRI’s)
- Sleep Disturbance: Mirtazapine or Trazodone
- Agitation: SSRIs or mood stabilizers (manic-type behaviors), Depakote
- Consider antipsychotics (black box warning increased risk of death for older adults with dementia-related psychosis) for behaviors that threaten safety
See “Delirium” section in Psychiatry for inpatient management recommendations.
For patients with driving concerns: “Driving Solutions of Tennessee" 615-806-0012